
Survival Rate of Stage 4 Colorectal Cancer: What The Numbers Really Mean
The 5-year relative survival rate for stage 4 colorectal cancer is approximately 14%.
However, this general statistic does not account for individual factors like age, overall health, and specific genetic mutations.
With advanced targeted therapies and surgical interventions, many patients now live significantly longer than historical averages suggest.
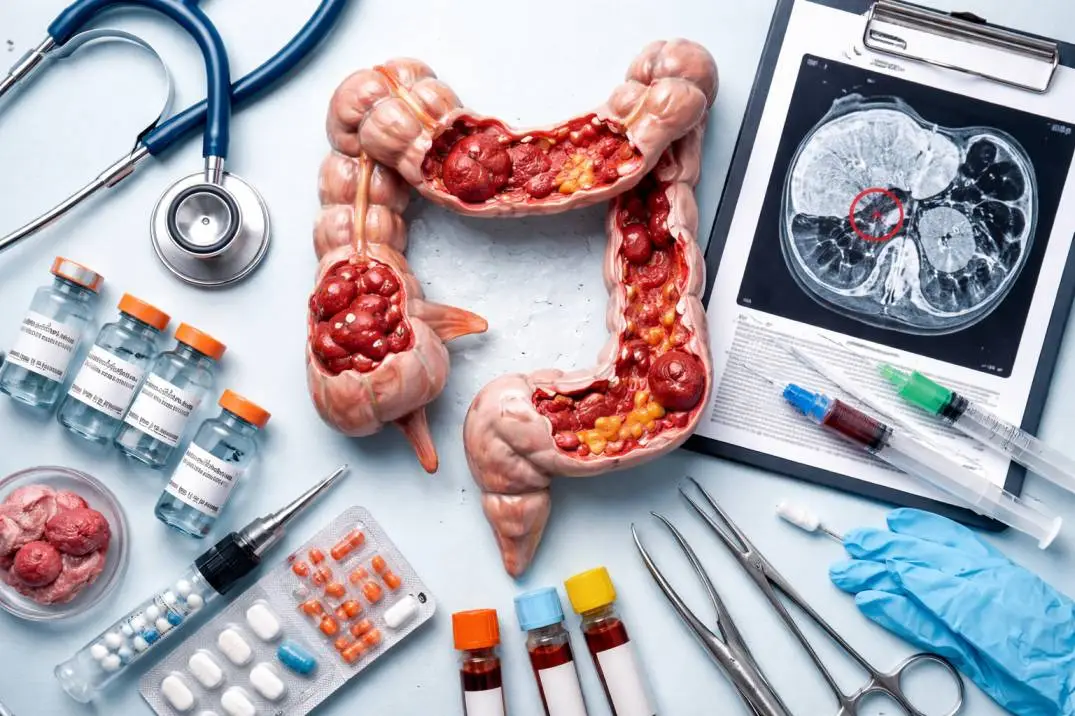
Quick Facts at a Glance
- Definition: Cancer that has spread from the colon or rectum to distant organs like the liver or lungs.
- Candidates for Treatment: Most patients are eligible for systemic therapy; select patients qualify for curative surgery (metastasectomy).
- Procedure Time: Chemotherapy cycles vary (often 2-3 weeks); surgery takes 3-6 hours.
- Recovery: Surgery requires 4-8 weeks; chemotherapy recovery is ongoing between cycles.
- Success Rate: Highly variable; surgical resection of liver metastases can boost 5-year survival to 40-50%.
- Cost Range: Variable depending on location and insurance, but comprehensive treatment plans are significant investments.
Why Survival Statistics Aren’t the Whole Story?

When you or a loved one receives a diagnosis of stage 4 colorectal cancer, the first question is almost always about time. You search for numbers. You look for percentages. You want to know where you stand.
While statistics provide a baseline, they look backwards at large groups of people treated years ago. They do not reflect your specific biology or the newest treatments available today.
In the past decade, the landscape of advanced colorectal cancer treatment has shifted dramatically. It is no longer just about palliative care.
For a growing number of patients, it is about chronic disease management and, in specific cases, curative intent.
This guide breaks down what survival rates actually mean, the factors that improve them, and the treatment options that are changing the outlook for stage 4 patients.
Understanding Stage 4 Colorectal Cancer
Stage 4 colorectal cancer, also known as metastatic colorectal cancer (mCRC), means the cancer cells have broken away from the original tumour in the colon or rectum.
They have travelled through the blood or lymph system to form new tumours in other parts of the body.
The most common sites for metastasis are:
- The liver (most common)
- The lungs
- The peritoneum (lining of the abdomen)
- Distant lymph nodes
Is Stage 4 Curable?
Historically, stage 4 was considered incurable. Today, doctors use the term “potentially curable” for certain patients.
If the metastases (spread) are limited to a few spots in the liver or lungs (oligometastatic disease), surgeons may be able to remove them completely.
When combined with chemotherapy, this approach offers the best chance for long-term survival.
What Affects Your Survival?
Why does one patient live for six months while another lives for ten years? Survival rates are averages, but your prognosis is personal. Several key factors influence outcomes.
1. Location and Number of Metastases
Patients with spread limited to the liver often have better outcomes than those with spread to multiple organs or the bones. If the tumours in the liver are resectable (removable by surgery), survival rates improve dramatically.
2. Genetic Profile (Biomarkers)
This is the most critical area of modern advancement. Your medical team should test your tumour for specific gene mutations.
- RAS and BRAF status: Knowing if you have these mutations helps doctors choose the right drugs.
- MSI-H/dMMR status: Patients with “high microsatellite instability” often respond exceptionally well to immunotherapy, a newer class of drugs that boosts the immune system.
3. Performance Status
This is a medical score of your general well-being and ability to perform daily activities. Patients who are active and maintain good nutrition generally tolerate aggressive treatments better, leading to longer survival.
4. Response to First-Line Therapy
How the cancer responds to the first round of chemotherapy is a strong predictor of long-term outcome. Shrinkage of tumours early on is a very positive sign.
A Patient Story: “Doctor, Can I Survive This?”
I remember a patient who came to me after being diagnosed with stage 4 colorectal cancer that had spread to the liver.
His first question was simple: “Doctor, can I survive this?”
I told him that stage 4 cancer is serious, but it does not mean that treatment has stopped being an option.
We started treatment and monitored his response. Fortunately, the cancer responded well, and after reassessing his scans, surgery became possible.
What stayed with me was how different his outlook became. He had initially seen “stage 4” as the end. We started seeing it as a treatment plan with several possibilities.
This is why I tell patients not to judge their future only by a survival percentage. Some patients with stage 4 colorectal cancer can live for many years, and selected patients may achieve long-term disease control or remission.
The important question is not only, “What is the survival rate?”
It is also, “What is possible in my case?”
Modern Treatment Options That Improve Your Survival
The 14% survival statistic is an average that includes patients who received no treatment or only older therapies. Modern medicine offers a multi-modal approach that pushes survival beyond historical limits.
Systemic Chemotherapy
This remains the backbone of treatment. Drugs circulate throughout the body to kill cancer cells. Regimens like FOLFOX or FOLFIRI are standard. While they have side effects, supportive care to manage nausea and fatigue has improved significantly.
Targeted Therapy
These drugs attack specific parts of cancer cells that make them different from normal cells.
- Anti-VEGF therapy (e.g., Bevacizumab): Stops the tumour from growing new blood vessels, essentially starving it.
- Anti-EGFR therapy (e.g., Cetuximab): Blocks proteins that tell cancer cells to divide (effective only in patients without RAS mutations).
Immunotherapy
For the small percentage of patients with MSI-H tumours, immunotherapy drugs like Pembrolizumab have been game-changers, sometimes offering durable remission where chemotherapy failed.
Surgery for Metastases (Metastasectomy)
This is the most impactful intervention for survival. If the primary tumour and the liver/lung spots can be surgically removed with clear margins, the 5-year survival rate can jump from the standard 14% to nearly 50%.
Liver-Directed Therapies
For patients who cannot have surgery, other techniques can control liver tumours:
- Ablation: Burning or freezing the tumour.
- Embolization: Blocking the blood supply to the tumour, sometimes delivering chemotherapy or radiation beads directly into the liver.
Why a Team Approach Matters ?
Treating stage 4 colorectal cancer is complex. It requires a team, not just a single doctor. Your care should be discussed by a tumour board that includes:
- Surgical Oncologists: To evaluate if tumours can be removed.
- Medical Oncologists: To manage drug therapies.
- Radiologists: To interpret scans accurately.
- Pathologists: To analyse the genetic makeup of the tumour.
Research consistently shows that patients treated at high-volume centres with multidisciplinary teams have better survival outcomes. They are more likely to be offered surgery and access to clinical trials.
How Can You Take Care of Your Emotional Health?
A stage 4 diagnosis is life-altering. The mental burden is just as heavy as the physical one.
- Seek Palliative Care Early: Palliative care is not just for end-of-life. It is specialised medical care for people living with a serious illness. It focuses on providing relief from the symptoms and stress of the cancer.
- Join Support Groups: Speaking with others who are navigating the same treatment decisions can be invaluable.
- Focus on ‘Quality’ Survival: Discussions with your doctor should not just be about extending life, but maintaining the quality of that life.
Questions to Ask Your Specialist
To ensure you are getting the best possible chance at improving your survival rate, ask your oncologist these questions:
- Have we tested my tumour for genetic mutations (RAS, BRAF, MSI)?
- Am I a candidate for liver or lung surgery? If not now, could chemotherapy make me a candidate later?
- Are there any clinical trials available for my specific type of cancer?
- What is the goal of our current treatment plan: curative or palliative?
Why Choose Dr. Aditya Kulkarni?
When facing advanced colorectal cancer, the expertise of your surgeon can define your trajectory.
Dr. Aditya Kulkarni is a renowned Gastrointestinal and Robotic Surgeon dedicated to providing world-class care for complex cancer cases.
He specialises in minimally invasive and robotic techniques that allow for precise removal of tumours with quicker recovery times.
Dr. Kulkarni does not just treat the disease; he treats the patient.
He believes in a personalised approach, reviewing every aspect of your genetic profile and scan results to determine if surgical intervention can improve your survival rate of stage 4 colorectal cancer.
His approach is rooted in honesty, cutting-edge science, and compassionate care. He works closely with a team of oncologists to ensure that surgery is timed perfectly with chemotherapy for the best possible outcome.
If you are looking for a second opinion or want to explore if surgery is an option for you, book a consultation today. Do not rely solely on general statistics—find out what is possible for your specific case.
Disclaimer: The content provided in this blog is for informational purposes only and does not constitute medical advice. Every patient is unique, and survival rates can vary significantly based on individual circumstances.
Always consult with a qualified healthcare professional for diagnosis and treatment options regarding the survival rate of stage 4 colorectal cancer.
Frequently Asked Questions About Stage 4 Colorectal Cancer Survival
1.Can you live 10 years with stage 4 colorectal cancer?
Yes, some people with stage 4 colorectal cancer live for 10 years or longer, particularly when the cancer responds well to treatment and metastatic tumours can be controlled or completely removed. Long-term survival is more likely in selected patients with limited metastases, favourable tumour biology, and good response to treatment. However, survival varies considerably from person to person.
2.Can stage 4 colorectal cancer go into remission?
Yes. Stage 4 colorectal cancer can sometimes enter complete remission, particularly when all visible cancer can be successfully removed or destroyed. Some patients may achieve long-term disease-free survival after treatment. However, remission does not guarantee that the cancer will never return, so regular follow-up is important.
3.What happens if chemotherapy stops working for stage 4 colorectal cancer?
If the cancer progresses despite the first treatment, it does not necessarily mean that treatment options have run out. Your oncologist may consider another chemotherapy combination, targeted therapy, immunotherapy when appropriate, a treatment based on specific tumour mutations, a clinical trial, or a local treatment such as surgery or ablation. The next step depends on how the cancer has changed and which treatments have already been used.
4.How fast does stage 4 colorectal cancer spread?
There is no single rate at which stage 4 colorectal cancer spreads. Some tumours progress relatively slowly, while others can grow or spread rapidly. The tumour’s biology, genetic characteristics, location and extent of metastases, and response to treatment all influence how quickly the disease progresses.
5.Can stage 4 colorectal cancer be treated without surgery?
Yes. Surgery is not appropriate or necessary for every patient with stage 4 colorectal cancer. Chemotherapy, targeted therapy, immunotherapy, radiation, ablation, and other liver-directed treatments may be used depending on where the cancer has spread and the patient’s overall condition. Surgery may become an option later if treatment shrinks the metastases enough to make them removable.
6.What are the signs that stage 4 colorectal cancer is getting worse?
Possible signs of progression include increasing abdominal pain, changes in bowel habits, unexplained weight loss, worsening fatigue, loss of appetite, increasing jaundice when the liver is significantly affected, or increasing breathlessness when the lungs are involved. However, symptoms alone cannot reliably determine whether cancer is progressing. Imaging scans and other tests are needed to assess treatment response.
7.How often should scans be done during treatment for stage 4 colorectal cancer?
The timing of scans depends on the treatment plan, symptoms, tumour behaviour, and the type of therapy being used. Many patients have imaging at regular intervals during systemic treatment to determine whether the cancer is responding, remaining stable, or progressing. Your oncologist will decide the appropriate interval for your specific situation.
8.Does age affect stage 4 colorectal cancer survival?
Age can influence treatment tolerance and overall prognosis, but age alone does not determine survival. A fit older adult may tolerate treatment better than a younger person with significant health problems. Doctors usually consider overall health, fitness, other medical conditions, nutritional status, tumour biology, and treatment response when estimating prognosis.
9.Can diet improve survival in stage 4 colorectal cancer?
A healthy, balanced diet can help maintain strength, nutrition, and treatment tolerance, but there is no specific food or diet proven to cure stage 4 colorectal cancer. Patients should be particularly careful about restrictive diets or unproven cancer diets that may lead to weight loss or nutritional deficiencies. A dietitian experienced in oncology can provide individualised nutritional advice.
10.Is stage 4 colorectal cancer always terminal?
No. Stage 4 colorectal cancer is a serious and potentially life-threatening disease, but it is not automatically an immediate terminal diagnosis. Some patients live for many years with controlled metastatic disease, while a smaller group with limited metastases may achieve long-term disease-free survival after aggressive treatment. Prognosis depends on the individual cancer rather than the stage alone.
11.What is the difference between stage 4A, 4B and 4C colorectal cancer?
Stage 4 colorectal cancer can be further classified according to the extent and pattern of distant spread. The exact staging system and categories can vary depending on the staging system being used. Your doctor can explain your specific stage based on which organs are involved, the number and location of metastases, and whether the spread can potentially be treated with surgery or other local therapies.
12.Can liver metastases from colorectal cancer be removed?
In selected patients, yes. Liver metastases may be removed surgically when they can be completely cleared while leaving enough healthy liver behind. The number, size, location, and distribution of the liver tumours, as well as the patient’s overall health and whether disease exists elsewhere, all influence whether surgery is possible. Some initially unresectable liver metastases may become removable after chemotherapy shrinks them.
13.What should I do if I have been told my stage 4 colorectal cancer is inoperable?
Being told that surgery is not possible at one point does not always mean surgery will never be possible. Some metastatic tumours can shrink after systemic treatment and may later become suitable for surgery or another local treatment. If you have limited metastatic disease, a review by a multidisciplinary team or a second opinion from a specialist colorectal or gastrointestinal cancer centre can help determine whether additional options exist.
14.Does the location of the primary colorectal tumour affect survival?
Yes. Whether the original cancer is located in the right or left side of the colon or in the rectum can influence prognosis and treatment choices. The tumour’s molecular characteristics and pattern of metastatic spread are also important. Your treatment plan should therefore consider the complete clinical and molecular picture rather than tumour location alone.
15.When should someone with stage 4 colorectal cancer consider a second opinion?
A second opinion can be particularly useful when there is uncertainty about treatment options, metastatic surgery, clinical trials, biomarker-directed treatment, or whether the cancer is potentially resectable. It can also help when treatment has stopped working or when you have been told that no surgical option exists. A second opinion does not necessarily mean changing doctors; it can provide another expert assessment of the available options.
16.How can I improve my chances of living longer with stage 4 colorectal cancer?
The most important steps are to understand the exact extent and biology of the cancer, complete appropriate biomarker testing, follow the recommended treatment plan, attend scheduled scans, maintain adequate nutrition and physical activity when possible, and discuss clinical trials or local treatments when appropriate. If metastases are potentially removable, getting an expert surgical assessment can also be important.
17.Is palliative care useful even when I am receiving cancer treatment?
Yes. Palliative care can be provided alongside active cancer treatment. It focuses on controlling symptoms such as pain, nausea, fatigue, appetite problems, and emotional distress while helping patients maintain quality of life. Receiving palliative care does not mean that cancer treatment has stopped or that a person is necessarily approaching the end of life.
18.What is the most important factor in predicting stage 4 colorectal cancer survival?
There is no single factor that accurately predicts survival for every patient. The extent and location of metastatic disease, whether all cancer can potentially be removed or controlled, tumour biology and biomarkers, overall health, and response to treatment all contribute to prognosis. This is why an individual’s outlook cannot be determined accurately from the general 5-year survival statistic alone.

Dr. Aditya Kulkarni
MS, DNB, FRCS, MCh (Surgical Gastroenterology & GI Oncology)
Dr. Aditya Kulkarni is a Consultant of Laparoscopic and Robotic Gastrointestinal, Hepato-biliary-pancreatic, and Cancer Surgeon at the Renowned Oasis Surgery Clinic Pune.